
Stop Asking “Is Third-Generation IVF Worth It?”: Those Who Truly Need It May Be Exactly the Ones Who Can’t Afford to Miss It
Is Third-Generation IVF Really Necessary? What You Actually Need to Understand First Is "Whether It's Right for You"
Recently, there has been growing discussion about whether third-generation IVF is truly necessary. After reading certain studies, some people have jumped to the conclusion that "third-generation IVF isn't useful." Others have even dismissed it as "a waste of money" or "an IQ tax."
But if you take a closer look at the study subjects, the scope of application, and what third-generation IVF technology actually does, you'll find that: The question has never been "Does third-generation IVF have value?" but rather—"Are you actually the type of person for whom third-generation IVF is appropriate?"
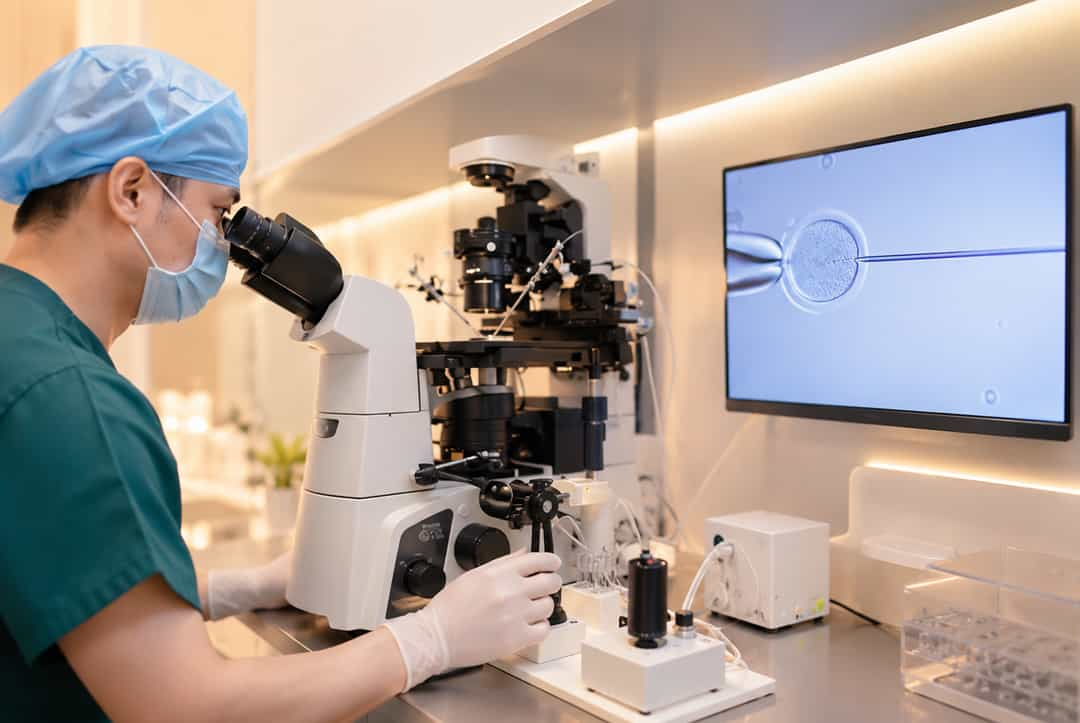
This is also what Global New Life has always hoped families considering third-generation IVF in Thailand would understand first. Third-generation IVF is not simply an "upgraded version" of first- or second-generation IVF, nor is it a mandatory procedure for every patient undergoing IVF. Its true significance lies in using preimplantation genetic testing (PGT) for the right candidates and appropriate medical indications, helping physicians obtain more information about the genetic status of embryos to inform subsequent embryo selection and family planning decisions.
So rather than debating "whether third-generation is good or not," it's more important to first understand: What problems does it actually address?
1. The Value of Third-Generation IVF That Is Difficult to Replace: Genetic Risk Management
For ordinary couples facing infertility, first- and second-generation IVF technologies can already resolve many fertilization-related issues. However, when one or both partners carry a clear genetic risk, the situation is entirely different. For example, if both partners carry pathogenic variants associated with certain monogenic disorders, or if there are chromosomal structural abnormalities, the pregnancy may face more complex genetic risks.
Common scenarios include: thalassemia, hemophilia, spinal muscular atrophy (SMA), certain forms of hereditary deafness, as well as chromosomal balanced translocations and Robertsonian translocations. For these families, the question may not be "Can we get pregnant?" but rather: How can we minimize the risk of passing a specific genetic condition on to the next generation? This is precisely the important application direction of PGT technology.
What is commonly referred to as "third-generation IVF" actually encompasses different types of preimplantation genetic testing. PGT-M primarily targets certain confirmed monogenic disorders; PGT-SR is mainly used for conditions related to chromosomal structural rearrangements; and PGT-A primarily assesses whether embryos have chromosomal number abnormalities.
In other words, the true value of third-generation IVF is not "making success rates higher for everyone," but rather providing more targeted embryonic genetic information based on different genetic risks. For families with clear genetic indications, this is something that first- and second-generation IVF may not be able to directly replace.
2. Why Are More and More People Learning About PGT-A as Age Advances?
Many families first encounter third-generation IVF in Thailand not because of a family genetic disorder, but because of age. Women planning to conceive after age 35, in particular, tend to pay more attention to embryonic chromosomal status. This is because as a woman's age increases, the risk of chromosomal abnormalities in oocytes rises accordingly—and an embryo that looks "good quality" morphologically does not necessarily mean its chromosomes are normal.
This is also a point that is easily misunderstood. Embryology laboratories typically assign morphological grades based on developmental speed, cell appearance, and degree of blastocyst expansion, but morphological grade and chromosomal status are not the same thing.
A morphologically beautiful embryo may still have chromosomal abnormalities; conversely, morphological grade is not the sole criterion for judging an embryo's full potential. Therefore, for some patients of advanced maternal age, those with recurrent pregnancy loss, or those with repeated implantation failure, a physician may discuss whether PGT-A has clinical significance based on the specific situation.
However, it must be emphasized here: Advanced maternal age ≠ PGT-A is mandatory. Whether screening is needed should be determined by considering ovarian reserve, the number of embryos obtainable, previous pregnancy history, miscarriage history, and the results of both partners' examinations.
3. For Those with Repeated Failure, the First Question to Answer Is "Where Does the Problem Actually Lie"
In assisted reproduction, there is another highly perplexing situation: a couple has undergone numerous tests with no obvious abnormalities detected, yet cycle after cycle of embryo transfer yields unsatisfactory results. Some families can conceive naturally but experience recurrent miscarriage or arrested embryonic development. In such cases, what causes the most anxiety is often not "finding a problem," but rather: never knowing where the problem is. This is because the factors affecting pregnancy outcomes are extremely complex.</||DSML||
Possible factors include embryonic chromosomes, uterine structure, endometrial condition, endocrine factors, male factors, and other medical issues. In some cases, PGT-A can provide information at the embryonic chromosomal level. For example, if a higher proportion of chromosomal abnormalities is found among the embryos obtained, the physician gains an additional important reference direction when analyzing the causes of previous failures.
If screened euploid embryos have been obtained but transfer still does not achieve the expected outcome, the physician may then focus attention on other factors.
It should be noted that PGT-A itself is not a universal test that diagnoses all "unexplained failures," nor can it rule out every cause of implantation failure or miscarriage. It provides information at the embryonic chromosomal level, not a "comprehensive check-up" of the entire reproductive system.
4. Why We Keep Emphasizing: Third-Generation Is Not "More Advanced" Than First- or Second-Generation
Many families preparing for IVF ask Global New Life: "Since we're going to do it anyway, wouldn't it be best to just choose third-generation?" The answer is not that simple.
"First, second, and third generation" are actually colloquial terms that have developed over time in China, and they can easily create the impression that "third generation is necessarily more advanced than second generation." But the problems they address are not the same.
- First-generation IVF typically refers to conventional IVF, where sperm and egg are fertilized in a laboratory environment;
- Second-generation typically refers to ICSI (intracytoplasmic sperm injection), which is mainly used for certain male factor issues or situations with fertilization障碍 risk;
- The so-called third generation primarily involves adding PGT on top of IVF to perform specific genetic testing on embryos.
So they are more like different tools, rather than a phone upgrading from the first generation to the third.
For those without clear genetic indications, who are younger, and have good ovarian reserve, it does not necessarily mean that undergoing PGT will guarantee a better outcome. Instead, factors such as the number of embryos, biopsy, testing costs, and the overall treatment protocol need to be considered. Therefore: Being able to do third-generation IVF does not mean you necessarily need it; and not doing third-generation IVF does not mean your protocol is "outdated."
5. The Real Questions to Ask Are Not "Should I Do Third-Generation?" but These
Before starting an IVF cycle, what matters more than choosing between "first, second, or third generation" is first gaining a clear understanding of both partners' baseline conditions.
For example:
- What is the woman's age?
- What are the AMH levels and antral follicle count?
- Is there a history of miscarriage, missed miscarriage, or repeated implantation failure?
- What is the male semen analysis like?
- Do either partner have chromosomal abnormalities?
- Is there a clear family history of genetic disease?
- In previous IVF cycles, what were the numbers of eggs retrieved, fertilization outcomes, blastocyst culture results, and embryo development?
Combined together, this information forms the essential foundation for determining a treatment plan.
Take two 38-year-old women: one may have good ovarian reserve and be able to obtain multiple blastocysts; another may have significantly diminished ovarian reserve, producing very few embryos per cycle. Same age does not mean they should necessarily follow the exact same protocol. This is why a truly professional assisted reproduction plan can rarely be decided based only on "age" or "a single AMH number."
6. Why Do Many Families Choose to Learn More About Third-Generation IVF in Thailand?
For families considering fertility treatment abroad, Thailand has become one of the more prominent assisted reproduction destinations in recent years.
What many families focus on is not just the phrase "third-generation IVF," but the ability to comprehensively compare hospitals, physicians, embryology laboratories, PGT protocols, language communication, travel arrangements to Thailand, and the overall service experience.
But one of the biggest differences between seeking treatment overseas versus domestically is the longer chain of information.
From organizing preliminary test results, selecting hospitals and physicians, to scheduling appointments, planning travel dates to Thailand, accommodation and transportation, translation and communication—and then managing each milestone after entering the cycle—everything requires advance coordination.
This is precisely the purpose of overseas patient coordination services.
Global New Life has long been dedicated to third-generation IVF in Thailand and overseas assisted reproduction services. What we aim to do is not simply tell clients "go do third-generation," but first help families clarify their own needs and baseline conditions, and only then explore the protocols offered by different hospitals and physicians.
Because truly responsible advice should never be: "Third-generation is more advanced, so you should do third-generation." It should be: "First look at what problems you need to solve, then decide which technology suits you better."
In Closing: The True Value of Third-Generation IVF Is "Being There Just When You Need It"
The debate over third-generation IVF can easily swing to two extremes. One extreme is: "Third-generation is the best—if you're doing IVF, you should go straight to third-generation." The other extreme is: "Studies have shown it's unnecessary, so third-generation is an IQ tax." Both interpretations are overly simplistic. PGT is not a universal technology, it cannot guarantee success with every transfer, and it cannot solve every problem that causes infertility, miscarriage, or arrested embryonic development. But for those with clear genetic risks, and for certain populations whom physicians have comprehensively evaluated as potentially benefiting from PGT, it does hold significant clinical value.
So, the real comparison in IVF has never been about "which generation is more powerful—first, second, or third," but rather which one is more suitable for you. For families currently considering third-generation IVF in Thailand, overseas fertility treatment, or cross-border family building, Global New Life always recommends: first understand your own physical condition, organize your past test results and reproductive history, and only then compare hospitals, physicians, and different assisted reproduction protocols. Don't blindly pursue what sounds "more advanced," and don't overlook a technology that is truly right for you. This, perhaps, is the value of third-generation IVF that deserves to be truly understood.

- Previous
- Next